
Learning that your pregnancy has been classified as high-risk can feel overwhelming, even frightening. We want you to know, from the very first appointment, that you are not alone. At Dr. Rad’s practice, we understand that pregnancy is already one of the most vulnerable and emotionally charged experiences of your life, and a high-risk diagnosis adds a layer of anxiety that no one should have to carry without expert support. Our goal is to give you clear, honest information, a personalized care plan, and the reassurance that comes from working with one of Los Angeles’ most experienced maternal-fetal medicine specialists.

What Is a High-Risk Pregnancy?
A high-risk pregnancy is one in which the mother, the baby, or both face a higher-than-average chance of complications before, during, or after delivery. The term does not mean that something will go wrong. It means you may need closer monitoring, more frequent prenatal care visits, and sometimes specialist involvement to support the best possible outcome for you and your baby.
What Qualifies a Pregnancy as High Risk?
If your doctor has used the phrase “high-risk pregnancy,” you may be feeling a wave of worry right now – and that’s completely understandable. But here’s the reassuring truth: being labeled high risk simply means your pregnancy needs a little extra attention and care. It doesn’t mean something will go wrong. It means you and your baby deserve closer monitoring from a specialist who truly knows what to look for.
So what actually qualifies a pregnancy as high risk? Generally speaking, a pregnancy is considered high risk when certain factors increase the likelihood of complications for the mother, the baby, or both. These factors typically fall into a few broad categories:
Maternal age: Pregnancies in women under 17 or over 35 carry elevated risks. If you’re an older first-time mom, you’re far from alone – and with the right care, outcomes can be excellent.
Pre-existing health conditions: Diabetes, high blood pressure, autoimmune disorders, heart disease, kidney disease, and thyroid conditions can all complicate a pregnancy.
Lifestyle factors: Smoking, alcohol use, obesity, or a history of substance use may place a pregnancy in the high-risk category.
Pregnancy-specific conditions: Issues that develop during pregnancy itself – such as preeclampsia, gestational diabetes, placenta previa, or carrying multiples – can also qualify a pregnancy as high risk.
Previous pregnancy complications: A history of preterm birth, miscarriage, or stillbirth is an important risk factor your care team will take seriously.
Assisted reproductive technology (ART). Pregnancies achieved through IVF or other fertility treatments carry a modestly higher risk of certain complications, including multiple gestation.
It’s also worth knowing that high-risk pregnancies are becoming more common, which makes access to a skilled maternal-fetal medicine specialist more important than ever. The good news? With the right support, most high-risk pregnancies result in healthy moms and healthy babies.
Common Risk Factors in Detail
Advanced Maternal Age
Women who give birth at 35 or older are considered to be of advanced maternal age (AMA). Risks vary within this group. Women aged 35 to 39 face a moderately elevated risk of chromosomal abnormalities, gestational diabetes, preeclampsia, and placental abruption. Women who conceive at 40 or older face a steeper increase in those same risks, along with a higher likelihood of cesarean delivery and postpartum hemorrhage.
Chromosomal abnormalities such as Down syndrome become significantly more common with advancing maternal age. At 35, the risk of carrying a baby with Down syndrome is approximately 1 in 350; by 40, that figure rises to roughly 1 in 100. For this reason, birth defect screening and genetic counseling are strongly recommended for women of advanced maternal age.
Screening options typically include cell-free DNA (cfDNA) testing, also known as non-invasive prenatal testing (NIPT), which can be performed as early as 10 weeks and screens for the most common chromosomal conditions with high accuracy. For patients who want a definitive answer, diagnostic procedures such as amniocentesis or chorionic villus sampling (CVS) are also available. Dr. Rad will walk you through every option so you can make an informed decision that feels right for you and your family.
The good news is that with attentive prenatal care, most women over 35 have healthy pregnancies and healthy babies. Practical steps that make a real difference include attending all scheduled prenatal visits, managing pre-existing conditions like hypertension or diabetes before and during pregnancy, maintaining a balanced diet, and promptly communicating any new symptoms to your care team. Dr. Rad works closely with patients of advanced maternal age to tailor a monitoring plan that addresses their specific risk profile, including early screening, more frequent ultrasounds, and a clear delivery plan. That personal touch – knowing your specialist is available 24/7 and genuinely invested in your outcome – is the Dr. Rad difference.
Gestational Diabetes
Gestational diabetes develops when the body cannot produce enough insulin to meet the increased demands of pregnancy, causing blood sugar levels to rise. It typically appears after 20 weeks and affects approximately 6 to 9 percent of pregnancies in the United States.
Risk factors include obesity, a family history of type 2 diabetes, a previous pregnancy affected by gestational diabetes, and being over 25 years of age. Polycystic ovary syndrome (PCOS), a sedentary lifestyle, and certain ethnic backgrounds – including Hispanic, Black, Native American, and Asian – are also associated with higher risk. Screening is performed using a glucose tolerance test, usually between 24 and 28 weeks of pregnancy. Women with multiple risk factors may be screened earlier, during the first trimester, to allow for prompt intervention.
When gestational diabetes is not well controlled, it raises the risk of preterm birth, a large baby (macrosomia), birth injuries, low blood sugar in the newborn, and, in severe cases, stillbirth. Babies born to mothers with poorly managed gestational diabetes also face a higher lifetime risk of obesity and type 2 diabetes themselves. For the mother, it increases the long-term risk of developing type 2 diabetes.
Management typically includes dietary changes, regular blood sugar monitoring, physical activity, and, in some cases, insulin therapy. Some patients may be prescribed oral medications such as metformin when insulin is not preferred. Alongside these measures, closer fetal surveillance – including additional ultrasound exams and non-stress tests – helps Dr. Rad monitor your baby’s growth and well-being throughout the third trimester. That level of attentive, personalized oversight is the Dr. Rad difference. With proper management, most women with gestational diabetes deliver healthy babies.
Preeclampsia
Preeclampsia is a serious pregnancy complication characterized by high blood pressure and signs of damage to other organ systems, most often the kidneys, which show up as elevated protein levels in the urine. It typically develops after 20 weeks of pregnancy and affects 5 to 8 percent of all pregnancies. Preeclampsia is one of the leading causes of maternal mortality worldwide, which is why early detection and careful monitoring are so important.
Risk factors include a first pregnancy, obesity, a history of high blood pressure or kidney disease, carrying multiples, advanced maternal age, and a personal or family history of preeclampsia. Warning signs include a sudden rise in blood pressure, severe headaches, visual disturbances, upper abdominal pain, rapid weight gain, and significant swelling of the hands and face.
Management depends on the severity of the condition and the baby’s gestational age. Mild preeclampsia may be managed with close monitoring, blood pressure medication, and fetal surveillance. Severe preeclampsia often requires hospitalization and may necessitate early delivery. If left unmanaged, preeclampsia can progress to eclampsia, which involves seizures, and can be life-threatening for both mother and baby.
Because preeclampsia can escalate quickly and without obvious warning, consistent monitoring is one of the most powerful tools available. At the Maternal Fetal Care Center, Dr. Rad uses state-of-the-art ultrasound technology to assess fetal growth and placental blood flow through Doppler studies, which can reveal early signs of placental insufficiency before symptoms become severe. Regular biophysical profiles and non-stress tests also evaluate how well the baby is tolerating the condition. For patients who prefer to be monitored from the comfort of their own home, Dr. Rad’s concierge at-home prenatal care service brings this level of expert surveillance directly to you – 24/7, whenever you need it. That personal touch, combined with cutting-edge diagnostic tools, is what sets high-risk pregnancy care at this level apart. That is the Dr. Rad difference.
If you have been diagnosed with preeclampsia, or if you carry risk factors that concern you, an early consultation with a maternal-fetal medicine specialist gives you the best possible foundation for a safe pregnancy. The sooner a management plan is in place, the more options you have – and the more confident you can feel walking into every appointment.
Obesity and Lifestyle Factors
Obesity before or during pregnancy raises the risk of gestational diabetes, preeclampsia, preterm birth, cesarean delivery, and birth defects. A body mass index of 30 or higher at the start of pregnancy is associated with a significantly elevated risk profile.
Smoking during pregnancy reduces oxygen delivery to the baby and is linked to preterm birth, low birth weight, placental abruption, and sudden infant death syndrome (SIDS). Alcohol use in pregnancy carries no established safe level and is associated with fetal alcohol spectrum disorders. Drug use, including opioid dependence, requires specialized management to protect both mother and baby during pregnancy and delivery.
If any of these factors apply to you, please know that our team approaches these conversations without judgment. Our only goal is to help you and your baby thrive.
Signs and Symptoms of a High-Risk Pregnancy
Knowing what to watch for during a high-risk pregnancy can genuinely make a difference in outcomes – and it’s one of the most important conversations we have with our patients. Some warning signs are easy to dismiss as “just pregnancy,” but when you’re managing high-risk pregnancy conditions, it’s always better to reach out and let your care team decide whether something needs attention. Think of it as your body sending you messages worth listening to.
Here are some of the most important signs and symptoms to take seriously:
Vaginal bleeding or unusual discharge – any amount of bleeding warrants a prompt call to your provider
Severe or persistent abdominal pain or cramping – especially if it doesn’t ease up with rest
Sudden swelling in your face, hands, or feet – this can be an early indicator of preeclampsia
Severe headaches or visual disturbances – blurred vision, seeing spots, or sudden sensitivity to light
Decreased fetal movement – if your baby feels quieter than usual after 28 weeks, don’t wait to check in
Fever above 100.4°F – infections during pregnancy can escalate quickly
Difficulty breathing or chest pain – never something to brush off
Signs of preterm labor – regular contractions before 37 weeks, pelvic pressure, or low back pain
If you’re experiencing any of these symptoms, please don’t hesitate. As a high-risk OB/GYN, Dr. Rad offers 24/7 availability – because peace of mind shouldn’t have office hours. That’s the Dr. Rad difference.
How Is a High-Risk Pregnancy Diagnosed and Monitored?
If you’ve been told you have a high-risk pregnancy, one of the first questions on your mind is probably: “So what happens next?” The good news is that a diagnosis of high-risk pregnancy doesn’t mean something will go wrong – it simply means your care team will watch over you and your baby more closely than a routine pregnancy. That extra attention is genuinely protective, and it makes a real difference in outcomes.
Diagnosis typically begins with a thorough review of your medical history, current health conditions, and any complications from previous pregnancies. From there, your specialist will build a monitoring plan tailored specifically to you. Common tools used to track high-risk pregnancies include:
Advanced ultrasound exams – State-of-the-art 3D and 4D high-definition ultrasound technology allows your doctor to assess fetal growth, anatomy, and placental health in remarkable detail. Early fetal scans can begin as early as 11 to 16 weeks.
Fetal echocardiogram – A specialized ultrasound that evaluates your baby’s heart structure and function, particularly important when cardiac anomalies are suspected.
Prenatal genetic testing – Including cell-free DNA screening, amniocentesis, or chorionic villus sampling to identify chromosomal conditions early.
Non-stress tests and biophysical profiles – These assess how well your baby is tolerating the pregnancy environment as you move into the third trimester.
Specialist consultations – A maternal-fetal medicine specialist, or perinatologist, coordinates your care and communicates closely with your broader healthcare team.
With concierge-level, 24/7 access to a renowned perinatologist like Dr. Rad, monitoring your high-risk pregnancy becomes a collaborative, personalized experience – not a stressful series of appointments. That is the Dr. Rad difference.
Warning Signs to Watch For During a High-Risk Pregnancy
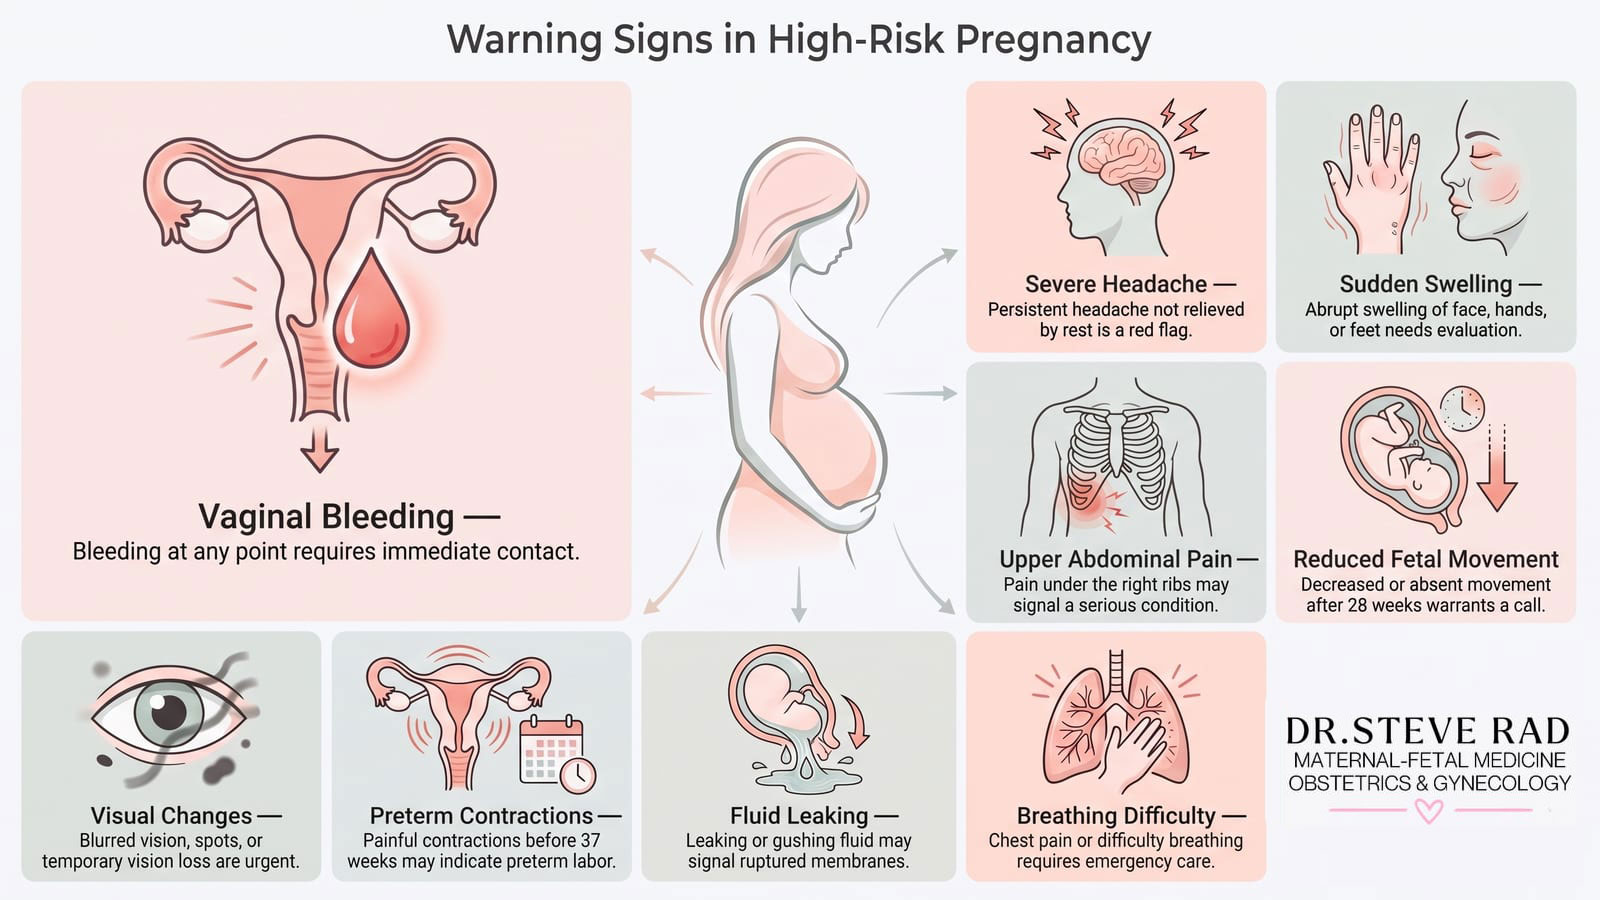
Even with close monitoring, it is important that you know which symptoms should prompt an immediate call to your provider or a visit to the emergency room. Contact Dr. Rad’s office or seek emergency care right away if you experience any of the following:
Vaginal bleeding at any point in pregnancy
Severe or persistent headache that does not respond to rest
Sudden swelling of the face, hands, or feet
Visual changes, including blurred vision, seeing spots, or temporary vision loss
Upper abdominal pain, especially under the ribs on the right side
Decreased or absent fetal movement after 28 weeks
Painful or frequent contractions before 37 weeks (a sign of preterm labor)
Leaking or gushing of fluid from the vagina (possible rupture of membranes)
Fever above 100.4 degrees Fahrenheit
Difficulty breathing or chest pain
Severe nausea and vomiting that prevents you from keeping food or fluids down (hyperemesis gravidarum)
Trust your instincts. If something feels wrong, it is always better to call and be reassured than to wait and wonder.
How High-Risk Pregnancies Are Monitored and Managed by Your Care Team
One of the most important things a high-risk pregnancy diagnosis means is that you will have access to a higher level of surveillance and support. Here is what that typically looks like in Dr. Rad’s practice.
Specialist Referral and Maternal-Fetal Medicine Care
A maternal-fetal medicine specialist, also called a perinatologist, is an OB-GYN with advanced training in managing complex pregnancies. Dr. Rad works alongside your primary OB or midwife, or, in some cases, takes over primary pregnancy management, to ensure every aspect of your care is coordinated. If you have been referred to our practice, it is because your provider recognizes that your pregnancy deserves this level of expertise.
Advanced Ultrasound and Fetal Monitoring
Detailed ultrasound is the cornerstone of high-risk pregnancy monitoring. Depending on your specific conditions, you may have ultrasounds every two to four weeks, or more frequently. These scans assess fetal growth, amniotic fluid levels, placental position and function, and fetal anatomy. For pregnancies at risk of fetal cardiac anomalies, a fetal echocardiogram provides a detailed view of the baby’s heart structure and rhythm.
A non-stress test (NST) measures the baby’s heart rate in response to its own movements and is a simple, non-invasive way to assess fetal well-being. A biophysical profile (BPP) combines an NST with an ultrasound assessment of fetal breathing, movement, muscle tone, and amniotic fluid volume to give a comprehensive picture of how the baby is doing.
Genetic Counselling and Prenatal Testing
For pregnancies at elevated risk of chromosomal abnormalities or inherited conditions, genetic counseling and birth defect screening are important tools. Non-invasive prenatal testing (NIPT) analyzes cell-free fetal DNA in the mother’s blood and can screen for conditions such as Down syndrome, Trisomy 18, and sex chromosome abnormalities as early as 10 weeks. When more definitive information is needed, amniocentesis, which involves sampling the amniotic fluid surrounding the baby, can provide a chromosomal diagnosis.
Management of Specific Conditions
Management plans are always individualized, but common interventions in high-risk pregnancies include:
Blood pressure medications to control gestational hypertension or preeclampsia
Insulin or oral medications to manage gestational diabetes
Cervical cerclage, a procedure that stitches the cervix closed, for patients with cervical insufficiency or a short cervix
Progesterone supplementation to reduce the risk of preterm birth in women with a history of preterm delivery
Anticoagulation therapy for patients with thrombophilias or a history of blood clots
More frequent prenatal care visits, sometimes weekly or twice weekly in the third trimester
Hospitalization or modified activity when conditions require closer observation
Planned early delivery when continuing the pregnancy poses greater risk than delivering the baby
Delivery Planning
For many high-risk pregnancies, the timing and method of delivery require careful planning. Dr. Rad works with you and your delivery team to determine the safest approach, whether that means a scheduled induction, a planned cesarean, or a carefully monitored vaginal delivery. The goal is always to balance the risks of continuing the pregnancy against the risks of early delivery, with your safety and your baby’s well-being at the center of every decision.
What You Can Do to Support a Healthy Pregnancy
While your medical team manages the clinical side of your care, there is a great deal you can do to support your own health and your baby’s development.
Attend every prenatal care appointment. Consistent monitoring is the single most important thing you can do in a high-risk pregnancy. Do not skip visits, even when you feel well.
Take your medications as prescribed. Whether it is a blood pressure medication, insulin, progesterone, or a blood thinner, these treatments are protecting you and your baby.
Eat a balanced, nutrient-rich diet. Focus on whole foods, adequate protein, and foods rich in folate, iron, and calcium. If you have gestational diabetes, work with a dietitian to manage your carbohydrate intake.
Avoid smoking, alcohol, and recreational drugs. These substances carry real risks for your baby at every stage of pregnancy.
Monitor fetal movement. After 28 weeks, pay attention to your baby’s movement patterns. A noticeable decrease in movement should prompt you to call your provider.
Manage stress. Chronic stress affects pregnancy outcomes. Lean on your support network, consider counseling if anxiety is significant, and communicate openly with your care team about how you are feeling emotionally as well as physically.
Know your warning signs. Review the list above, and don’t hesitate to seek care if something feels wrong.
We treat all patients as VIPs, ensuring you feel cared for and supported every step of the way. That is the Dr. Rad difference.

AMNIOTIC FLUID ISSUES
Amniotic fluid is the liquid that surrounds and protects an unborn baby inside the uterus. It plays a crucial role in the baby’s development. However, there can be issues related to the amniotic fluid during pregnancy. Here are a few:
High-Risk Pregnancy Conditions: A Complete Reference Guide to Terminology
The sections below provide a brief description of the full range of conditions Dr. Rad manages. This library is designed to be a reference you can return to as questions arise throughout your pregnancy. If you see your condition listed here, know that Dr. Rad has extensive experience managing it and is ready to guide you every step of the way.
Absent Cavum Septum Pellucidum
The absence of the cavum septum pellucidum means the cerebrospinal fluid has leaked out of the ventricles into the space between the brain and the surrounding membrane. This condition is called hydrocephalus.
Achondroplasia
Achondroplasia is a genetic disorder that results in slowed skeletal growth. The primary feature of achondroplasia is dwarfism.
Agenesis of Corpus Callosum
The corpus callosum is a bundle of nerve fibers connecting the left and right hemispheres of the brain. It plays a vital role in interhemispheric communication, allowing us to coordinate our actions across both sides of the body.
Amniotic Band Syndrome (ABS)
Amniotic Band Syndrome (ABS) is a rare condition where amniotic bands wrap around the baby’s arm, leg, fingers, or toes, restricting blood flow. The condition causes severe deformities in babies.
Antiphospholipid Syndrome
Antiphospholipid syndrome (APLS) is an autoimmune disorder that causes abnormal blood clotting. It can result in miscarriage, stillbirth, preterm delivery, and preeclampsia. Management typically involves anticoagulation therapy throughout pregnancy.
Antithrombin Deficiency
Antithrombin deficiency is a rare hereditary thrombophilia that increases the risk of abnormal blood clots. Patients are at higher risk of thrombosis, pulmonary embolism, and fetal death. Anticoagulation therapy is typically recommended during pregnancy.
Bleeding in Pregnancy
Bleeding during pregnancy can occur for several reasons, including placenta previa, placental abruption, uterine fibroids, or cervical incompetence. New or irregular bleeding during pregnancy should always be investigated promptly.
Bowel Obstruction
A bowel obstruction is a blockage in the bowels. This can be caused by improper formation of the bowels or by twisting or improper rotation of the bowels during fetal development. Babies born with a bowel obstruction need immediate intervention.
Brain Tumors
Brain tumors are cancerous growths inside the brain. Pregnant women should be aware of the symptoms of brain tumors and seek medical attention immediately if they experience them, as some symptoms overlap with common pregnancy complaints and can be missed.
Bronchopulmonary Sequestration
Bronchopulmonary sequestrations (BPS) are rare congenital anomalies characterized by an abnormal mass of non-functioning lung tissue that forms during fetal development. Large BPSs can lead to breathing problems and life-threatening complications.
CCAM (Congenital Cystic Adenomatoid Malformation)
A congenital cystic adenomatoid malformation (CCAM) is an abnormality of one or more lung lobes in which the lobe forms as a fluid-filled sac, called a cyst, which does not function as normal lung tissue. CCAMs develop with equal frequency on either lung but rarely occur on both sides. Most cases are diagnosed via prenatal ultrasound before the child is born.
CDH (Congenital Diaphragmatic Hernia)
Congenital diaphragmatic hernia (CDH) refers to a hole in the diaphragm, the muscle that separates the organs in the chest from those in the abdomen. During fetal development, other organs can move into the chest cavity through this hole, and babies with CDH may have underdeveloped lungs.
Cervical Insufficiency / Cervical Incompetence
Also known as cervical incompetence, cervical insufficiency is characterized by premature dilation of the cervix during pregnancy. If untreated, this results in early pregnancy loss. Cervical cerclage, a procedure that stitches the cervix closed, is a common and effective intervention.
Short Cervix
During pregnancy, the cervix lengthens and then shortens again in preparation for delivery. A short cervix can become too short too early in pregnancy, resulting in early labor or pregnancy loss.
Chorioangioma
Chorioangioma is a benign tumor of the placenta, seen in approximately 0.5 to 1 percent of pregnancies. Large chorioangiomas can affect fetal blood flow and require monitoring.
Cleft Lip / Cleft Palate
A cleft lip or palate is a birth defect where the upper lip and roof of the mouth do not fully close during fetal development. Babies and children with cleft palate can have food or liquids pass through the nose if the condition is not treated or managed.
Clubfoot
Clubfoot is a condition where the foot is turned inward or outward. This deformity can be detected as early as 12 weeks of gestation, but diagnosis is confirmed at birth.
Coarctation of the Aorta
Coarctation is a narrowing or blockage of blood vessels that occurs during fetal development. The condition usually affects the aorta, the main artery from the heart. Newborns with this condition may experience chest pain, shortness of breath, fatigue, dizziness, fainting, and leg swelling.
Congenital Heart Defects
Congenital heart defects (CHDs) are heart conditions a baby is born with. About 1 percent of babies in the U.S. are born with a heart defect, the severity of which varies widely. A fetal echocardiogram is the primary tool used to diagnose cardiac anomalies before birth, allowing families and care teams to plan appropriately.
Conjoined Twins
Conjoined twins are babies born physically connected to each other. They may share one or more internal organs. This rare condition requires highly specialized prenatal monitoring and delivery planning.
Cystic Hygroma
Cystic hygroma is a benign tumor that develops from the lymphatic system. They usually appear at birth or during infancy. The cyst is filled with fluid and can cause swelling and discomfort.
Dandy-Walker Malformation
Dandy-Walker Malformation (DWM) is a rare congenital disorder characterized by enlargement of the fourth ventricle. Also known as Dandy-Walker Syndrome or Cerebellar Hypoplasia, DWM involves underdevelopment of the middle part of the cerebellum, cystic enlargement of the fourth ventricle, and enlargement of the base of the skull.
Down Syndrome
Down syndrome is a genetic condition caused by having three copies of chromosome 21 instead of two. This causes differences in brain development, muscle tone and coordination, vision, hearing, speech, learning, and memory. Birth defect screening and genetic counseling can identify the risk of Down syndrome before birth.
Echogenic Bowel
Echogenic bowel is a condition where the intestines appear bright or white on ultrasound. This can be perfectly normal; however, several medical problems could also cause this finding, and further evaluation is typically recommended.
Factor V Leiden Mutation
Factor V Leiden mutation (FVL) is a genetic condition that increases the risk of developing abnormal blood clots in the legs or lungs. It is one of the most common inherited thrombophilias and requires careful monitoring and often anticoagulation during pregnancy.
Fetal Anemia
Fetal anemia is a condition where the fetus has low levels of red blood cells or hemoglobin. This occurs during pregnancy because the fetus does not produce enough red blood cells or because they are destroyed faster than they are replaced. The condition can cause serious health problems for both mother and baby.
Fetal Arrhythmias (VT, PAC, PVC)
Fetal arrhythmias are abnormal heart rhythms that occur during pregnancy. In most cases, a too-slow or too-fast heartbeat is temporary. Less than 2 percent of fetal heartbeat irregularities represent true fetal arrhythmias requiring intervention.
Fetal Congenital Birth Defects
A congenital condition is one a baby is born with. These include heart defects, cleft lip and palate, spina bifida, genetic disorders, and more. Genetic testing and proper fetal monitoring can sometimes catch these problems early, allowing for planning and intervention.
Fetal Growth Restriction (IUGR)
Intrauterine growth restriction (IUGR) is a condition where the baby does not grow at a normal rate during pregnancy. It can be caused by problems with the placenta, maternal health conditions such as high blood pressure or diabetes, chromosomal abnormalities, or multiple gestation. Babies with IUGR are at increased risk of preterm birth, low oxygen levels, and difficulties after delivery.
Monitoring for IUGR relies heavily on serial ultrasounds, which track the baby’s growth measurements over time and assess blood flow through the umbilical cord using Doppler studies. When the care team detects growth restriction early, it can increase fetal monitoring, optimize maternal nutrition and blood pressure control, and plan delivery timing to minimize risk. Many babies diagnosed with IUGR go on to thrive with the right support in place.
Gastroschisis
Gastroschisis is a rare birth defect in which part of the intestines protrudes through the abdominal wall and extends outside the body. The baby needs surgery after birth to move the intestines back inside the body. Even after treatment, babies with gastroschisis can have trouble eating, digesting, and absorbing nutrients.
Gestational Hypertension
Gestational hypertension is a condition that occurs during pregnancy where blood pressure rises above 140/90 mmHg. This is usually temporary and resolves after delivery, but it requires monitoring because it can progress to preeclampsia.
History of Blood Clots
Blood clots occur when platelets stick together and form a plug or clot. The improper formation of these plugs can cause serious health problems such as heart attacks, strokes, deep vein thrombosis, pulmonary embolism, and even death. Pregnancy itself increases the risk of clotting, making a prior history of blood clots an important factor in prenatal care planning.
Holoprosencephaly
Holoprosencephaly is a rare genetic disorder characterized by incomplete development of the brain and face. The condition occurs in about 1 in 16,000 births and is caused by gene mutations that affect neural tube closure during fetal development.
Hydronephrosis
Hydronephrosis is a condition in which urine backs up into the kidneys, causing them to swell and enlarge. It can be caused by a blockage or an anatomical defect. Severe hydronephrosis can result in kidney damage if untreated.
Hyperemesis Gravidarum
Hyperemesis gravidarum is a severe form of nausea and vomiting in pregnancy that goes far beyond typical morning sickness. It can lead to dehydration, weight loss, and nutritional deficiencies if not treated. In severe cases, hospitalization and intravenous fluids or nutrition may be required.Inflammatory Bowel Disease, Crohn’s Disease, and Ulcerative Colitis
Crohn’s disease and ulcerative colitis are chronic conditions that affect the GI tract. Symptoms include abdominal pain, diarrhea, rectal bleeding, fatigue, fever, joint pain, skin rashes, and weight loss. Active disease during pregnancy requires careful coordination between gastroenterology and maternal-fetal medicine.
Isoimmunization
Also known as alloimmunization, isoimmunization occurs when the baby and carrier have different blood types. The mother’s immune system reacts to the baby’s incompatible blood proteins by attacking them.

FETAL ISSUES
Fetal issues during pregnancy encompass a range of conditions and complications that can affect the development and health of the unborn baby. They can be caused by various factors, including genetic abnormalities, maternal health conditions, infections, and exposure to certain medications or harmful substances, and can affect multiple systems.
Lower Urinary Tract Obstructions
A lower urinary tract obstruction (LUTO) is a blockage of the fetus’s urinary tract. Urine build-up can lead to permanent organ damage.
Lupus
Lupus is an autoimmune disease that affects the body’s connective tissue, including the skin, joints, blood vessels, lungs, and kidneys. Symptoms include fatigue, fever, joint pain, skin rashes, mouth sores, kidney problems, and hair loss. Lupus can increase the risk of preeclampsia, preterm birth, and fetal growth restriction.
Micrognathia
Micrognathia is a congenital malformation of the jawbone. The lower jawbone is smaller than normal, which can cause feeding or breathing problems. It may resolve on its own or may require intervention.
Monochorionic Diamniotic Twins
Monochorionic diamniotic (MCDA) twins are rare, occurring in only 0.5 percent of twin pregnancies. The twins share a placenta but have their own amniotic sacs. They are at higher risk of complications due to their shared blood supply, including twin-to-twin transfusion syndrome and twin anemia polycythemia sequence.
MTHFR Mutation
Methylenetetrahydrofolate reductase (MTHFR) is an enzyme that breaks down the amino acid homocysteine. Mutations in the MTHFR gene, which codes for this enzyme, can interfere with the enzyme’s ability to function normally or completely inactivate it. Elevated homocysteine levels are associated with an increased risk of pregnancy complications.
Multiple Gestation Complications
Multiple pregnancies, including twins, triplets, and higher-order multiples, are associated with higher rates of maternal morbidity and mortality than single pregnancies. Risks include preterm birth, preeclampsia, gestational diabetes, fetal growth restriction, and twin-specific complications such as TTTS and TAPS. Pregnancies achieved through assisted reproductive technology (ART) carry an elevated risk of multiple gestation.
Multiple Sclerosis
MS is a chronic disease that affects the central nervous system and leads to neurological symptoms such as vision problems, muscle weakness, fatigue, numbness or tingling, and difficulty walking. Pregnancy can affect the course of MS, and medication management requires specialist input.

FETAL BLOOD ISSUES
Fetal blood issues can range from relatively common conditions, such as blood type incompatibilities between mother and fetus, to more rare and serious conditions, like fetal anemia.

BRAIN ISSUES
Fetal brain issues refer to a range of conditions that can affect the development and function of a baby’s brain during gestation. These conditions can be due to genetic abnormalities, infections, trauma, or other unknown causes.
Oligohydramnios
Oligohydramnios is a condition where there is insufficient amniotic fluid in the uterus. This causes fetal distress and can result in premature labor or miscarriage.
Omphalocele
Omphalocele is a rare congenital defect in which part or all of the abdominal wall fails to close during fetal development. Some of the baby’s organs end up outside of the body, enclosed in a protective membrane. Other birth defects usually accompany this condition.
Opioid Dependence
Opioids are synthetic drugs derived from opium and include prescription medications such as oxycodone, hydrocodone, and codeine. Opioid dependence during pregnancy requires a compassionate, multidisciplinary approach. Medication-assisted treatment is safe and effective and significantly reduces risks for both mother and baby.
Placenta Accreta
Placenta accreta is a condition where placental tissue grows abnormally into the uterine wall. It is associated with a significantly elevated risk of postpartum hemorrhage and often requires a planned cesarean delivery with a multidisciplinary surgical team.
Placenta Previa
Placenta previa is a condition where the placenta covers the cervix, meaning the baby cannot pass through the birth canal. The condition occurs in approximately 2 out of every 1,000 pregnancies and generally develops early in pregnancy. It is typically managed with pelvic rest and planned cesarean delivery.
Polycystic Kidneys
Polycystic kidney disease (PKD) is a rare genetic disorder characterized by cysts growing inside the kidneys. These cysts can enlarge the kidney or impair kidney function.
Polyhydramnios
Polyhydramnios is a condition where amniotic fluid builds up in the uterus. Most causes are mild and do not require treatment; however, severe cases can result in premature delivery.
Postpartum Hemorrhage and Massive Bleeding
Postpartum hemorrhage (PPH) is when blood loss during childbirth exceeds 500 ml. This can occur any time after delivery but usually happens within 24 hours of giving birth. It is a leading cause of maternal mortality and requires rapid intervention.
Preterm Labor
Labor occurring before 37 weeks of gestation is preterm and may result in complications or incomplete fetal development. Preterm birth is one of the leading causes of neonatal morbidity and mortality. The risk increases with advanced maternal age, multiple pregnancies, obesity, diabetes, smoking during pregnancy, alcohol use, and certain infections.
Preterm Premature Rupture of Membranes (PPROM)
PPROM is a condition where the amniotic sac ruptures before 37 weeks of pregnancy. This results in a higher risk of infection and preterm labor and requires immediate medical evaluation.
Prothrombin Gene Mutation
Prothrombin gene mutation (PGM) is a genetic condition that causes abnormal blood clotting and is another inherited thrombophilia that requires evaluation and management during pregnancy.
Pyelectasis
Pyelectasis occurs during pregnancy when excess urine collects in the baby’s kidneys. It is more common in males and is often detected on routine prenatal ultrasound.
Recurrent Pregnancy Loss
Recurrent Pregnancy Loss occurs when a woman has three or more consecutive losses before 20 weeks of gestation. Recurrent miscarriage increases the likelihood of future pregnancy loss, and a thorough evaluation to identify underlying causes, including thrombophilias, chromosomal abnormalities, and uterine structural issues, is an important first step.
Renal Agenesis
Renal agenesis is a rare congenital condition where the kidneys fail to develop properly during gestation. In some cases, the affected kidney fails to form. A prenatal ultrasound may detect or suggest this condition, which is confirmed after birth.
Rheumatoid Arthritis
Rheumatoid arthritis (RA) is an autoimmune disease in which the immune system attacks the joints, causing inflammation. Medication management during pregnancy requires careful review, as some RA treatments are not safe for use during pregnancy.
Seizure Disorder
Seizures are sudden episodes of abnormal electrical activity in the brain. They can cause convulsions, muscle contractions, or loss of consciousness. Managing a pre-existing seizure disorder during pregnancy requires careful medication review, as some anti-seizure medications carry risks for fetal development.
Seizure Disorder in Pregnancy
Some patients without a prior seizure disorder may experience seizures during pregnancy. These can cause serious complications for both mother and baby and require prompt evaluation.
Spina Bifida
Spina bifida is a neural tube defect where part or all of the spinal cord does not form properly during pregnancy. Increased folic acid intake before and during early pregnancy can help prevent the condition.
Stillbirth
Stillbirth is fetal death after 20 weeks of pregnancy, before or during birth. This may occur due to maternal health conditions, pregnancy complications, placental abruption, or several other pregnancy or delivery problems. For families who have experienced stillbirth, Dr. Rad’s Rainbow Clinic offers compassionate support for subsequent pregnancies.

Call (844) 473-6100 or click here to schedule online

LUNG ISSUES
Fetal lung issues refer to various conditions that can affect the development and function of an unborn baby’s lungs. These issues can range from minor to serious, impacting the baby’s ability to breathe and oxygenate blood after birth. Advancements in neonatal medicine have significantly improved the prognosis for many of these issues.

BLADDER ISSUES
Fetal bladder issues refer to problems related to the development and function of the bladder in an unborn baby. These can be detected during routine prenatal ultrasound scans. One such issue is:
Call (844) 473-6100 or click here to schedule online

CERVICAL ABNORMALITY ISSUES
The cervix is the bottom part of the uterus that opens into the vagina. During pregnancy, the cervix should be long and firm to hold the fetus safely inside the womb. Unfortunately, several cervical problems can arise during pregnancy, such as:

FACIAL ABNORMALITY ISSUES
Fetal facial abnormalities are conditions that affect the development of the face in the unborn baby. They can range from minor and easily treatable to more serious conditions that can cause significant functional challenges.
Tetralogy of Fallot
Tetralogy of Fallot is a rare condition caused by a combination of four congenital heart defects that cause oxygen-poor blood to leave the heart and move to the rest of the body. Babies with tetralogy of Fallot often have blue skin discoloration, among other serious symptoms.
Thrombocytopenia
Thrombocytopenia is a condition where the platelet count is too low. This can cause bleeding problems, as platelets help stop bleeding. It can occur as a pregnancy-specific condition or as a manifestation of an underlying disorder.
Thyroid Disease
Thyroid disorders are common in women of childbearing age, affecting nearly 2 percent of American women. Symptoms include fatigue, depression, hair loss, dry skin, constipation, difficulty sleeping, and menstrual irregularities. Both hypothyroidism and hyperthyroidism require careful management during pregnancy to protect fetal brain development and prevent complications.
Transposition of the Great Arteries
Transposition of the great arteries is a congenital heart defect where the main pulmonary artery connects to the left ventricle instead of the right ventricle. This creates a shortage of oxygen-rich blood to the body. Without treatment, serious complications or death can occur.
Trisomy 18
Trisomy 18 is a rare chromosomal disorder that occurs during pregnancy. The baby has three copies of chromosome 18 instead of two. Babies with this condition are usually born small with some physical differences and intellectual disabilities.
Venous Thromboembolic Disease (VTE)
Venous thromboembolic disease is a condition where blood clots form inside veins or arteries. This can happen in the legs, arms, pelvis, lungs, or abdomen. The risk of developing VTE increases during pregnancy and in the postpartum period, making prevention and early detection critical.
Call (844) 473-6100 or click here to schedule online

GI ISSUES
Fetal gastrointestinal (GI) issues refer to a group of conditions that affect the development and function of an unborn baby’s digestive system. Some of these conditions are minor and can be managed after birth, while others may require immediate attention and even surgery after the baby is born.

HEART ISSUES
Fetal heart issues cover a range of conditions that can impact the development and function of an unborn baby’s heart. These can include structural defects, rhythm disturbances, or functional problems, all varying in severity. Some issues can have minor implications and require little or no intervention, while others can be life-threatening and necessitate immediate medical attention or even surgery after birth.

KIDNEY ISSUES
Fetal kidney issues refer to a group of conditions affecting the development and function of an unborn baby’s kidneys. The kidneys are vital organs that filter waste products from the blood, maintain electrolyte balance, and produce urine. Many of these issues can be detected during prenatal ultrasound scans, allowing for proper planning and preparation for treatment.

MATERNAL AUTOIMMUNE DISEASES IN PREGNANCY
Autoimmune diseases refer to conditions in which a patient’s immune system mistakenly attacks their own body tissues. These conditions can pose unique challenges and risks — especially during pregnancy. Depending on the specific autoimmune disease, these risks can range from preterm birth and low birth weight to more serious complications.

MATERNAL HEMATOLOGIC ISSUES
Maternal hematologic issues refer to disorders affecting a pregnant woman’s blood and blood-forming tissues. These can encompass a variety of conditions and can have varying degrees of impact on the mother and baby’s health.
Ventricular Septal Defect
Babies with ventricular septal defects are born with a hole between the heart’s lower chambers. An atrial septal defect is a hole between the heart’s upper chambers. Either condition disrupts the flow of oxygen-rich blood and may cause serious problems depending on its size.
Ventriculomegaly
Ventriculomegaly is the enlargement of the brain ventricles, the fluid-filled cavities inside the skull. This condition occurs when there is too much fluid in the brain, or the ventricles appear large because the surrounding brain tissue is too small.
Call (844) 473-6100 or click here to schedule online

MATERNAL NEUROLOGICAL ISSUES
Maternal neurological issues during pregnancy refer to disorders affecting the nervous system, which includes the brain, spinal cord, and peripheral nerves. These conditions can impact a woman’s health and well-being and the course and outcome of her pregnancy.

MATERNAL PREGNANCY CONDITIONS
Pre-existing maternal medical conditions can impact pregnancy outcomes. In addition, pregnancy can cause new medical complications for the pregnant parent. These conditions can affect various body systems and have diverse implications for the mother and baby’s health.
Call (844) 473-6100 or click here to schedule online

PLACENTA ISSUES
Placental problems refer to a variety of conditions that affect the placenta. The placenta is a crucial organ that provides oxygen and nutrients to the developing fetus while removing waste products. When complications arise, they can potentially impact the health of both mother and baby, leading to issues such as preterm birth, low birth weight, and, in severe cases, stillbirth.
Vasa Previa
Vasa previa is a rare pregnancy complication where fetal umbilical cord blood vessels run too close to the cervix. The vessels are at risk of rupture at the onset of labor, which can result in stillbirth. If detected early through prenatal ultrasound, the fetal survival rate is 97 percent.

SKELETAL ISSUES
Fetal skeletal issues refer to conditions that can affect the development and formation of an unborn baby’s skeletal system, including bones and cartilage. These issues can range from minor anomalies to severe disorders affecting the baby’s mobility and overall health.
Call (844) 473-6100 or click here to schedule online

TWIN COMPLICATIONS
Twin complications during pregnancy refer to potential health challenges that can arise when a woman carries more than one fetus. While many twin pregnancies progress without major issues, they are inherently more complex and carry a higher risk of certain complications. These can affect the mother’s health, the babies’ development, or both.
Twin Anemia Polycythemia Sequence (TAPS)
TAPS is a rare condition that occurs in twins that share a placenta. There are unequal blood counts between the twins, with one twin at risk of anemia and the other at risk of a too-high blood count (polycythemia). TAPS can develop spontaneously or as a complication following laser treatment for TTTS. Serial ultrasounds with Doppler blood flow measurements are used to monitor for this condition in monochorionic twin pregnancies.
Twin Reversed Arterial Perfusion (TRAP Sequence)
TRAP sequence is a rare complication of twins that share a placenta. One twin has a nonexistent or improperly formed heart, forcing the other twin’s heart to provide blood for both. Only one twin will fully develop and be able to live outside the womb. Intervention options include minimally invasive procedures to interrupt the blood flow to the acardiac twin and protect the healthy twin’s heart.
Twin-to-Twin Transfusion Syndrome (TTTS)
TTTS is a rare pregnancy condition affecting identical twins or other multiples who share one placenta. Uneven blood vessel distribution within the shared placenta causes one twin to receive too little blood and nutrients, risking malnourishment and organ failure, while the other receives too much, placing strain on the heart and risking cardiac complications. The Quintero staging system grades TTTS by severity, and treatment options range from close monitoring to fetoscopic laser surgery to separate the shared blood vessels. Early detection through regular ultrasound surveillance of monochorionic pregnancies is critical to achieving the best outcomes.
Call (844) 473-6100 or click here to schedule online
Managing a High-Risk Pregnancy: What to Expect
If you’ve been told you have one of the many high-risk pregnancy conditions, it’s completely natural to feel overwhelmed. The good news is that with the right specialist and a clear plan, most high-risk pregnancies result in healthy outcomes for both mom and baby. Here’s what management typically looks like – and what you can expect along the way.
First, you’ll likely be referred to a maternal-fetal medicine specialist (also called a perinatologist) who focuses exclusively on high-risk pregnancies. This specialist works alongside your regular OB/GYN to create a personalized care plan tailored to your specific situation. Think of it as having an extra layer of expert support in your corner.
You can expect more frequent prenatal visits than a typical pregnancy. Depending on your condition, this might mean appointments every one to two weeks rather than once a month. These visits often include advanced monitoring tools like state-of-the-art 3D and 4D ultrasound exams, fetal echocardiograms, non-stress tests, and detailed biophysical profiles to keep a close eye on your baby’s growth and wellbeing. Twin and multiple pregnancies, for example, require especially close surveillance throughout all three trimesters.
Some patients may be advised to modify their activity levels or, in certain cases, rest more than usual. Your care team will also put a detailed delivery plan in place well in advance, including decisions about timing, delivery method, and which hospital setting is safest for you and your baby.
At the Maternal Fetal Care Center, Dr. Rad offers 24/7 availability – including home and telemedicine visits – so you always have access to expert guidance when you need it most. That personal touch is what makes all the difference during a vulnerable time.
















