
What is a multiple pregnancy?
A multiple pregnancy, or multiple gestation, means carrying two or more fetuses. Multiples account for about 3% of all births in the United States, according to the Centers for Disease Control. Risk factors include a family history of twins, maternal age over 30, and fertility treatments such as in vitro fertilization (IVF). The rate of twin births has risen sharply over the past few decades, largely driven by the wider use of assisted reproductive technology – meaning more families than ever are navigating the unique challenges a multiple gestation brings.

Because complications during twin pregnancy are significantly more common than in singleton pregnancies, working with a perinatologist – a maternal-fetal medicine specialist – from early on is one of the most important decisions you can make. A key factor is chorionicity: whether your twins share a placenta (monochorionic) or each has their own (dichorionic) fundamentally changes your risk profile and how closely you need monitoring. Identical twins are more likely to share a placenta, which raises the stakes considerably. Fraternal twins almost always have separate placentas, which generally means a lower – though still elevated – level of risk compared to a singleton pregnancy.
Chorionicity and amnionicity: why placenta type matters
Before discussing individual complications, it helps to understand chorionicity and amnionicity, because the placenta type your twins share determines their risk level.
Fraternal (dizygotic) twins come from two separate eggs and two separate sperm. They are always dichorionic-diamniotic (DCDA): each baby has its own placenta and its own amniotic sac. This is the lower-risk configuration.
Identical (monozygotic) twins arise from a single fertilized egg that splits. Depending on when the split occurs, they may be:
Dichorionic-diamniotic (DCDA): separate placentas, separate sacs – similar risk profile to fraternal twins.
Monochorionic-diamniotic (MCDA): one shared placenta, separate sacs – significantly higher risk of twin-to-twin transfusion syndrome and selective fetal growth restriction.
Monochorionic-monoamniotic (MCMA): one shared placenta, one shared sac – the highest-risk configuration, with added danger of cord entanglement.
Ultrasound determines chorionicity, ideally in the first trimester. Knowing it early shapes every monitoring and management decision that follows.
Why is multiple gestation high risk?
The most significant risk is preterm labor. More than 60% of twins and nearly all higher-order multiples are born before 37 weeks. Premature babies are born before their organs are fully developed, typically require time in the neonatal intensive care unit (NICU) for help with breathing, feeding, temperature regulation, and infection control, and face elevated risks of long-term developmental challenges.
About 25% of twin pregnancies are complicated by intrauterine growth restriction (IUGR), sometimes called fetal growth restriction. In monochorionic twins, unequal sharing of placental blood flow can cause selective fetal growth restriction, where one twin receives significantly fewer nutrients than the other.
Twins also carry a higher overall risk of miscarriage. Vanishing twin syndrome – where one embryo is reabsorbed in the first trimester, often without symptoms – occurs in a meaningful proportion of twin conceptions, leaving a healthy singleton pregnancy behind.
Chorionicity: why placenta type changes everything
Not all twin pregnancies carry the same level of risk, and one of the most important factors is chorionicity – whether the twins share a placenta or have one each. Fraternal (dizygotic) twins always have two separate placentas and two separate amniotic sacs, making them dichorionic-diamniotic (DCDA). Identical (monozygotic) twins are more variable: depending on when the fertilized egg splits, they may share a placenta (monochorionic) or even, in rare cases, share both a placenta and an amniotic sac (monoamniotic). Monochorionic twins face a significantly higher rate of complications during twin pregnancy because a shared placenta means shared blood vessels – and that shared circulation is the root cause of several serious conditions described below.
Twin-specific complications: TTTS, monochorionic risks, and more
Once you understand why chorionicity matters, the next step is understanding the specific complications that can arise – particularly for monochorionic twins who share a placenta. These are the conditions that truly set complications during twin pregnancy apart from anything a singleton pregnancy involves.
Twin-to-twin transfusion syndrome (TTTS) is one of the most serious. It occurs when blood vessels within a shared placenta create an unequal flow between the two babies – one twin (the “donor”) pumps blood to the other (the “recipient”) without receiving enough in return. The donor twin becomes anemic and growth-restricted, while the recipient twin is overwhelmed with fluid, developing polyhydramnios and putting strain on its heart. Left unmonitored, TTTS can be life-threatening for both babies. Fortunately, with frequent ultrasound surveillance – something Dr. Rad prioritizes using state-of-the-art 3D/4D imaging – it can be caught early and managed effectively.
Twin anemia-polycythemia sequence (TAPS) is a subtler version of the same imbalance, where one twin becomes severely anemic while the other develops abnormally thick blood. It can develop spontaneously or after TTTS treatment.
Twin reversed arterial perfusion (TRAP) sequence, also called acardiac twinning, is rare but striking – one twin lacks a functioning heart entirely and survives only because the other twin’s heart pumps blood for both. This places enormous strain on the healthy twin’s cardiovascular system.
Monochorionic twins also face higher risks of selective intrauterine growth restriction (sIUGR), where one twin receives significantly less nutrition than the other due to unequal placental sharing. All of these conditions underscore why specialized maternal-fetal medicine care isn’t just helpful for twin pregnancies – it’s essential.
Selective fetal growth restriction in monochorionic twins is closely related to TTTS but involves unequal placental territory rather than active blood transfer. Fetal surveillance with biophysical profiles and Doppler flow studies guides timing of delivery.
Anemia is more common in twin pregnancies for both mother and fetuses. Maternal anemia results from the increased blood volume demands of two growing babies. Fetal anemia, particularly in the donor twin of a TTTS pair, can be severe enough to require intervention.
Polyhydramnios and oligohydramnios – too much or too little amniotic fluid – frequently accompany TTTS (the recipient sac becomes fluid-overloaded while the donor sac shrinks) but can also occur independently. Both conditions are monitored by ultrasound measurement of amniotic fluid index and can trigger preterm labor or require amnioreduction.
Monoamniotic twins and cord entanglement
In the rarest form of identical twinning, both babies share not only a placenta but also a single amniotic sac. These monoamniotic (or “mono-mono”) twins face a unique hazard: because no membrane separates them, their umbilical cords can become entangled. Cord entanglement is present in virtually all monoamniotic twin pregnancies and can restrict or cut off blood flow to one or both babies without warning. For this reason, monoamniotic twins require highly specialized monitoring – often including inpatient observation in the third trimester – and are typically delivered by planned cesarean section between 32 and 34 weeks.
Acardiac twin (twin-reversed arterial perfusion, or TRAP sequence) is a rare but life-threatening condition in which one twin has no functioning heart and is sustained entirely by the other. Fetal therapy centers can intervene.
Conjoined twins occur when a monozygotic egg splits very late and incompletely. This is rare, but early ultrasound can identify it and allow for careful planning with a multidisciplinary team.

Call (844) 473-6100 or click here to schedule online
Maternal complications of a twin pregnancy
Carrying two babies places substantially greater demands on your body, and conditions that can arise in any pregnancy become more likely with multiples. Key maternal complications include:
Gestational hypertension: High blood pressure during pregnancy is more common in twin gestations and requires close monitoring.
Preeclampsia: A serious condition involving high blood pressure, protein in the urine, and potential organ damage. Twin pregnancies roughly double the risk compared to singletons.
Gestational diabetes: Elevated blood sugar during pregnancy is more prevalent when carrying multiples.
Placental abruption: The placenta detaching from the uterine wall before delivery, which can compromise fetal oxygen supply.
Placenta previa: The placenta covering the cervix, which increases bleeding risk and typically requires a planned C-section.
Polyhydramnios: Excess amniotic fluid, which can cause preterm labor and maternal discomfort.
Cervical length shortening: A shortened cervix is a key predictor of preterm birth; cervical length screening is standard in twin prenatal care.
Delivery complications in twin pregnancies
The greatest delivery risk remains preterm birth. Importantly, some of the maternal and fetal conditions described above – severe preeclampsia, placental abruption, uncontrolled diabetes, and certain cases of TTTS or severe growth restriction – can only be resolved by delivering the babies early. This clinical reality is easy to overlook: delivery is not just a risk; it is sometimes the treatment. Having a perinatologist who can weigh that decision carefully is essential.
Patients carrying multiples are also at increased risk of postpartum hemorrhage. Because this is a known risk, close monitoring after delivery is standard practice. Cesarean delivery (C-section) is more common with twins and may be planned in advance or performed urgently if complications arise during labor.
Newborns delivered prematurely – which describes the majority of twins – often spend time in the NICU. Common newborn challenges include respiratory distress syndrome, feeding difficulties, jaundice, and temperature instability. Most premature twins do well with appropriate NICU support, and outcomes continue to improve as neonatal care advances.
Monitoring and managing twin pregnancy complications
When it comes to complications during twin pregnancy, early detection genuinely changes outcomes – and that means a monitoring schedule that looks quite different from a singleton pregnancy. A typical monitoring plan includes:
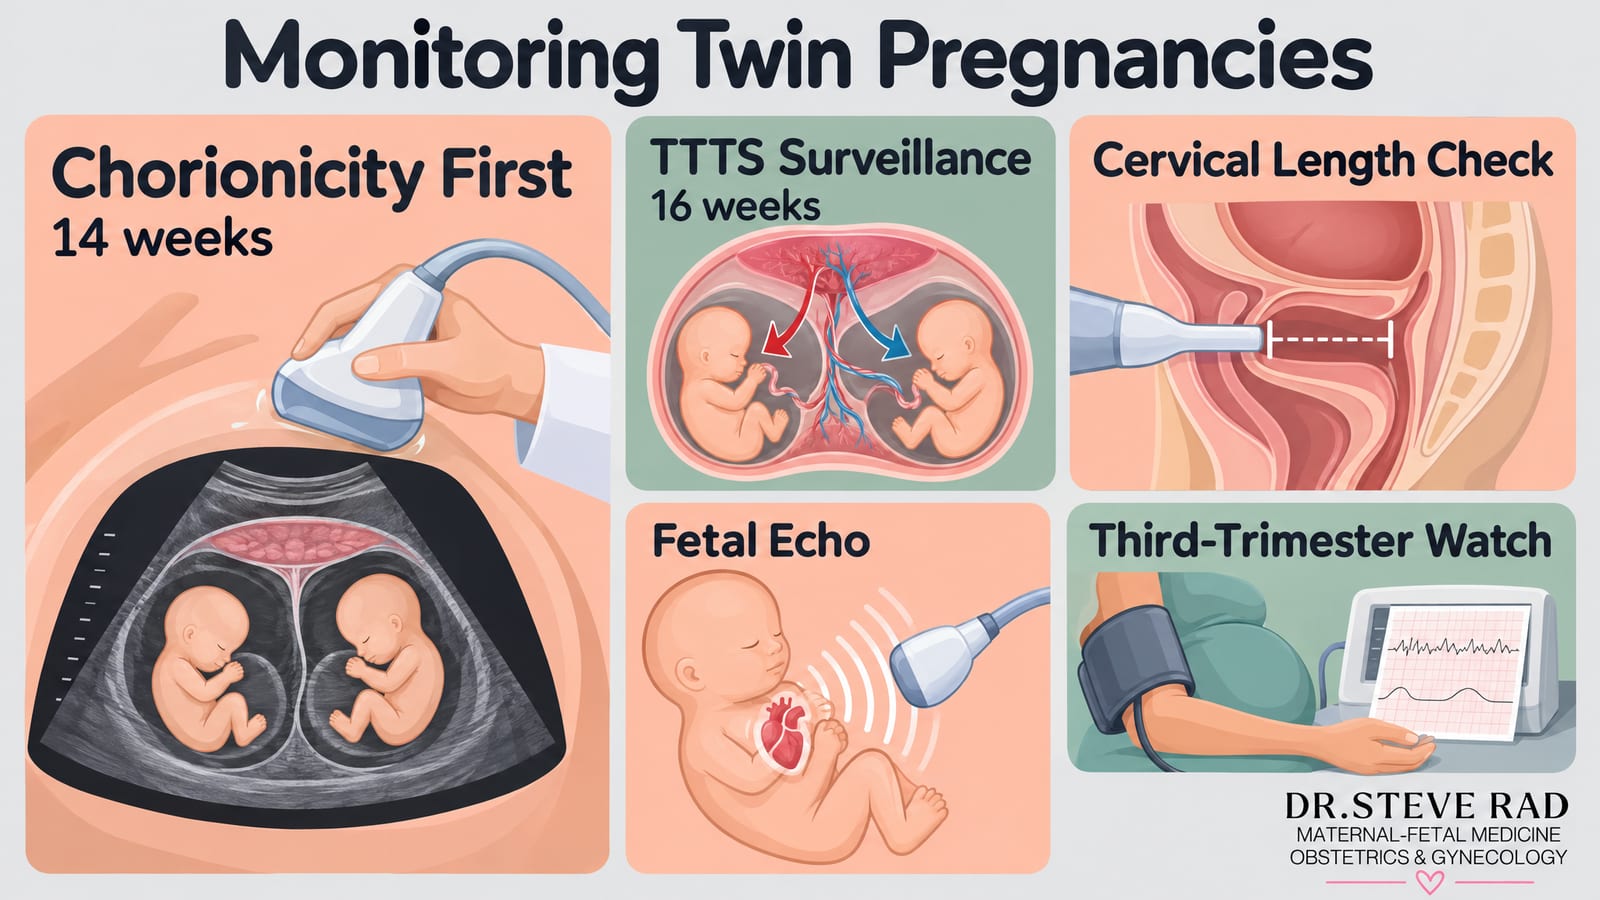
Early ultrasound to confirm chorionicity and amnionicity, ideally before 14 weeks.
Serial growth ultrasounds every 4 weeks for DCDA twins. For monochorionic twins sharing a placenta, surveillance for twin-to-twin transfusion syndrome often begins as early as 16 weeks and continues every two weeks throughout the second trimester, because TTTS can progress rapidly and the window for intervention is narrow.
State-of-the-art 3D and 4D ultrasound technology plays a central role here. Detailed imaging allows a high-risk OB/GYN to assess amniotic fluid levels in each sac, monitor fetal growth discordance, evaluate umbilical cord blood flow through Doppler studies, and check placental positioning – all in a single visit.
Measuring cervical length, typically between 18 and 24 weeks, helps identify mothers at elevated risk for preterm labor, allowing for timely interventions like progesterone supplementation or a cervical cerclage.
Fetal surveillance, including biophysical profiles and Doppler flow studies, when growth restriction or TTTS is suspected.
Fetal echocardiography for monochorionic twins at risk of cardiac complications from TTTS. A fetal echocardiogram is commonly recommended for monochorionic twins, since shared placental circulation can place added strain on developing hearts.
Genetic counseling and, when appropriate, prenatal genetic testing to screen for chromosomal conditions.
Biophysical monitoring. Providers closely track maternal blood pressure and urine protein to catch preeclampsia before it escalates. Non-stress tests and biophysical profiles become routine in the third trimester to confirm both babies are thriving.
When a complication is identified, management ranges from increased monitoring and bed rest to in-utero procedures such as laser surgery or amnioreduction, through to carefully timed early delivery. The goal is always to keep both babies in the womb as long as safely possible while protecting the health of the mother.
Dr. Steve Rad, MD, FACOG, is a maternal-fetal medicine specialist with deep expertise in high-risk obstetrics and twin pregnancy management. As the father of premature twin girls born from his wife’s own high-risk pregnancy, he has sat on both sides of the NICU experience – and that perspective shapes the care and compassion he brings to every patient. Having a maternal-fetal medicine specialist coordinate this level of care – someone who understands the full picture of why high-risk pregnancies are on the rise and what proactive monitoring can prevent – gives twin families the best possible foundation for a healthy outcome. That personal touch, combined with 24/7 availability, is the Dr. Rad difference.
Call (844) 473-6100 or click here to schedule online

Written by Dr. Rad Education Team

Medically Reviewed by Dr. Steve Rad
















